How do you distinguish these zoonoses in an exam vignette?
A zoonosis is an infection transmitted between animals and humans. For this group, start with the route of exposure before examining the fever pattern. Animal products contaminated with anthrax spores, unpasteurised dairy products carrying Brucella, and water contaminated with animal urine carrying Leptospira create different clinical stories. Occupation can be a useful bridge between an apparently nonspecific fever and the causative organism.
| Clue | Most useful association | Organism morphology |
|---|---|---|
| Wool or hide processing; painless black eschar | Anthrax | Large Gram-positive rods, often in chains |
| Raw dairy; livestock exposure; prolonged fever with joint pain | Brucellosis | Small Gram-negative coccobacilli |
| Contaminated water; fever, myalgia and conjunctival suffusion | Leptospirosis | Thin spirochetes |
Do not use a single exposure as an absolute rule. A veterinarian can encounter more than one zoonotic pathogen, and both anthrax and brucellosis can involve inhalational occupational exposure. Combine exposure with the lesion, laboratory appearance and pattern of organ involvement. In a clinical question, the distinction between uncomplicated fever and shock, respiratory failure or renal injury also determines the urgency of treatment.
What identifies Bacillus anthracis in the laboratory?
Bacillus anthracis is a spore-forming, Gram-positive bacillus. Large square-ended rods in chains give the classic boxcar appearance. The organism is characteristically nonmotile and nonhaemolytic on blood agar. These properties help distinguish it from other Bacillus species, but a suspected isolate requires reference laboratory confirmation rather than a casual identification based on appearance alone.
The characteristic colony has irregular filamentous projections described as a medusa head. This is a colony appearance, whereas boxcar describes the bacilli seen microscopically. Keep those levels separate in image questions: a plate photograph asks about colony morphology, a stained smear asks about cellular morphology, and a lesion photograph asks about the clinical syndrome.
An unusual virulence feature is the poly-D-glutamic acid capsule. It is a polypeptide capsule, unlike the polysaccharide capsules commonly discussed for other pathogens. The capsule helps the organism evade host defences. Spores account for environmental persistence and entry into the host; the vegetative organism produces the toxins responsible for much of the subsequent tissue injury.

How do the anthrax toxin components act?
Anthrax has a tripartite toxin system: protective antigen, oedema factor and lethal factor. Protective antigen enables the other factors to enter cells. Its name can mislead students into choosing it as a naturally protective host response; it is a bacterial toxin component and an important antigenic target.
| Component or combination | Mechanism | Consequence |
|---|---|---|
| Protective antigen | Facilitates entry of the enzymatic factors | Delivery component |
| Oedema factor with protective antigen | Adenylyl cyclase activity increases intracellular cyclic AMP | Oedema and impaired host responses |
| Lethal factor with protective antigen | Zinc-dependent metalloprotease cleaves MAP kinase kinases | Cellular injury, vascular dysfunction and shock |
Link the mechanism to the patient. Marked swelling around an anthrax lesion is consistent with toxin-mediated oedema; severe systemic disease reflects more than local bacterial growth. Toxins can continue to contribute to deterioration even while antimicrobial treatment targets the organism. This explains why systemic anthrax management may require antitoxin and intensive supportive care in addition to antibiotics.
Why is inhalational anthrax called woolsorter disease?
Woolsorter disease is the classic name for inhalational anthrax acquired while handling contaminated wool and other animal materials. Inhaled spores enter through the respiratory route and can produce severe mediastinal disease. A widened mediastinum in an exposed worker is a key clue; the question is not simply describing ordinary community-acquired pneumonia.
| Form | Exposure or route | Characteristic presentation |
|---|---|---|
| Cutaneous anthrax | Spores enter through skin breaks | Painless lesion progressing to a black eschar with surrounding oedema |
| Inhalational anthrax | Inhaled aerosolised spores | Systemic illness with haemorrhagic mediastinitis, pleural effusions and respiratory compromise |
| Gastrointestinal anthrax | Ingestion of contaminated food | Abdominal illness or oropharyngeal disease |
| Injectional anthrax | Injection of contaminated material | Deep soft-tissue infection and systemic toxicity |
Cutaneous anthrax may begin as a papule or vesicular lesion before forming the eschar. The combination of a dark centre, relative lack of pain and striking surrounding oedema is more useful than the dark colour alone. A black lesion is not automatically anthrax; the exposure history and overall clinical pattern still matter.
Systemic anthrax can involve shock or meningitis. The presence of neurological findings, severe respiratory disease or systemic toxicity moves the case beyond a local skin infection. Exam questions may ask for the organism, the toxin, the route of acquisition or the immediate management principle from the same occupational vignette. Identify which layer the question is testing before choosing an answer.
Which animal exposures and clinical features suggest Brucella?
Brucella organisms are Gram-negative, nonmotile, non-spore-forming, facultative intracellular coccobacilli. Transmission occurs through unpasteurised dairy, direct contact with infected animals and inhalation of contaminated aerosols. Abattoir workers, veterinarians and laboratory personnel are important occupational groups. Unlike anthrax, the characteristic environmental persistence mechanism is not spore formation.
| Species | Classic animal association | Revision cue |
|---|---|---|
| Brucella melitensis | Goats and sheep | Raw goat or sheep dairy exposure |
| Brucella abortus | Cattle | Cattle-associated infection |
| Brucella suis | Pigs | Swine exposure |
| Brucella canis | Dogs | Canine-associated infection |
The clinical illness is often prolonged and nonspecific: fever, sweats, malaise, arthralgia and fatigue. Undulant fever, Mediterranean fever and Malta fever are traditional names associated with brucellosis. The fever label is a recall clue rather than a requirement that every patient show a perfectly oscillating temperature chart.
Intracellular survival in cells of the reticuloendothelial system helps explain hepatosplenic involvement, persistent infection and relapse. Osteoarticular disease, including sacroiliitis or spondylitis, is a useful complication to recognise. Endocarditis and neurological involvement represent complicated disease and change treatment planning. A prolonged febrile illness with livestock exposure therefore warrants more than a generic label of viral fever.
How are brucellosis diagnosis and treatment linked to intracellular survival?
Culture and serology support diagnosis because symptoms alone are insufficiently specific. Blood cultures may take time to become positive. Bone marrow culture can have a higher yield because organisms are concentrated in the reticuloendothelial system. Standard agglutination testing, Rose Bengal testing and ELISA are useful serological approaches; interpretation depends on exposure, local epidemiology and the clinical picture.
Alert the laboratory when brucellosis is suspected. Brucella can cause laboratory-acquired infection through aerosols, so specimen processing requires appropriate containment. This is an exam-relevant link between microbiological diagnosis and occupational infection prevention. A laboratory exposure is also a different management question from treatment of an already symptomatic patient.
Treatment generally uses combination antibiotics with activity against intracellular organisms. Doxycycline with rifampicin is a familiar uncomplicated adult regimen; an aminoglycoside-containing regimen is another approach. Complicated disease, pregnancy and childhood require individualised choices. Avoid treating a memorised combination as universal across all of these groups.
The management principle is prolonged, appropriately selected combination therapy rather than a brief course or routine monotherapy. Relapse is a major reason adherence and follow-up matter. Focal complications should be sought when symptoms persist or localise. For an exam stem asking why combination therapy is preferred, intracellular persistence and relapse risk are the relevant concepts.
How does Leptospira cause disease after contaminated-water exposure?
Leptospira is a spirochete transmitted through the urine of infected animals. Contaminated water or soil can expose humans through damaged skin and mucous membranes. The animal may appear healthy while shedding the organism. Flood-water, agricultural and freshwater exposures are therefore useful prompts to ask about animal urine contamination rather than requiring a history of an obvious animal bite.
The illness can resemble a nonspecific febrile syndrome with headache, myalgia and gastrointestinal symptoms. Conjunctival suffusion is a valuable clue when present. Severe disease may involve jaundice, acute kidney injury, bleeding, respiratory failure and haemodynamic collapse. The term Weil disease refers to the severe icteric syndrome; it should not be used as a synonym for every mild Leptospira infection.
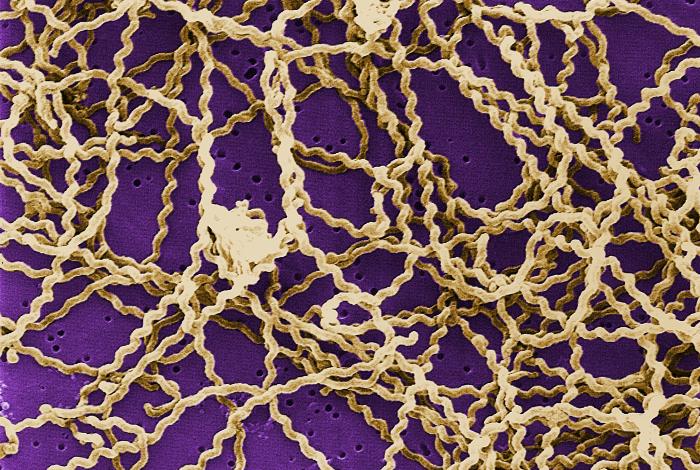
Aseptic meningitis can occur during an immune phase. This is why fever after a water exposure followed by meningeal symptoms should keep leptospirosis in the differential. The illness can affect multiple systems, so renal and liver function, blood counts, coagulation and respiratory status are clinically relevant alongside pathogen testing.
Which tests and treatment principles are useful for leptospirosis?
Leptospirosis can be supported by specialised culture and serological testing, including the microscopic agglutination test. Routine bacterial culture conditions are not an adequate substitute for a pathogen-specific diagnostic plan. The choice of specimen and test depends on illness timing and availability; interpret a negative early test in the context of the exposure and clinical findings.
Treat suspected leptospirosis promptly when the clinical suspicion is strong. Mild outpatient disease may be treated with an appropriate oral antibiotic such as doxycycline, while severe disease needs hospital assessment and intravenous therapy, commonly penicillin or ceftriaxone. These names are revision anchors, not a replacement for assessing contraindications, pregnancy, age and organ dysfunction.
Supportive care can be as important as pathogen-directed treatment in severe infection. Monitor fluid balance, renal function, bleeding and oxygenation. Acute kidney injury and respiratory compromise require escalation; a student should not choose an outpatient plan solely because the organism is known. In a management vignette, severity and the affected organs are decisive.
Prevention follows the transmission route: reduce contact with urine-contaminated water, cover skin breaks, use protective equipment during occupational exposure and control animal-related sources. This contrasts with pasteurisation for dairy-associated brucellosis and controls on infected animals and contaminated animal products for anthrax.
Which other zoonotic bacteria are asked alongside these three?
| Organism | Disease | High-yield anchor |
|---|---|---|
| Yersinia pestis | Plague | Associated with rats; bubonic form; diagnosed by culture |
| Francisella tularensis | Tularaemia | Highly infectious gram-negative coccobacillus; skin inoculation gives ulceroglandular disease (ulcer plus tender regional nodes), inhalation gives pneumonia; ticks and flies can transmit |
| Coxiella burnetii | Q fever | Obligate intracellular, gram-negative, pleomorphic; doxycycline is used, with hydroxychloroquine added for vascular complications; case fatality about 2% acute and 20% chronic |
Use the same exposure-first approach as for anthrax, brucellosis and leptospirosis: identify the animal, the route of entry and the organism morphology before choosing the test or drug.
Which comparison traps should you revise together?
| Question target | Correct anchor | Common trap |
|---|---|---|
| Anthrax capsule | Poly-D-glutamic acid | Calling every bacterial capsule polysaccharide |
| Medusa head | Anthrax colony morphology | Confusing the colony with a stained bacillus |
| Woolsorter disease | Inhalational anthrax | Choosing cutaneous anthrax from wool exposure alone |
| Undulant fever with raw dairy | Brucellosis | Expecting a diagnostic fever pattern in every patient |
| Urine-contaminated water and jaundice with renal injury | Leptospirosis; severe disease may be Weil disease | Equating all leptospirosis with Weil disease |
| Combination therapy and relapse | Brucella intracellular persistence | Choosing a short antibiotic monotherapy course |
For a rapid revision pass, cover the diagnosis column and explain each association aloud. Then reverse the direction: given the organism, name its morphology, an exposure route, a major complication and the diagnostic approach. This makes the same facts usable in microbiology identification, medicine vignettes and pharmacology treatment questions.