What is the essential difference between cephalhaematoma and caput?
The classic birth-injury comparison is an anatomical-plane question. Cephalhaematoma, also spelt cephalohematoma, is a collection of blood beneath the periosteum of a cranial bone. Caput succedaneum is oedematous swelling in the superficial scalp above the epicranial aponeurosis. The location determines the boundary of the swelling.
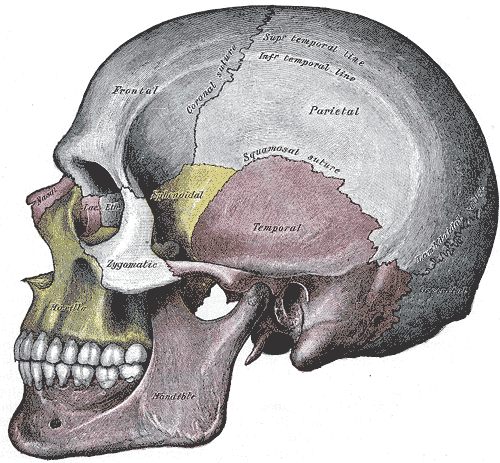
A cephalhaematoma is limited by the attachments of the periosteum at sutures, so a single collection does not cross cranial suture lines. Caput lies in a superficial plane where fluid can spread across these boundaries. Its swelling is therefore less sharply defined and can cross sutures and the midline.
| Feature | Cephalhaematoma | Caput succedaneum |
|---|---|---|
| Contents | Subperiosteal blood | Superficial scalp oedema, sometimes bruised |
| Plane | Between skull and periosteum | Above the epicranial aponeurosis |
| Suture crossing | No, for a single collection | Yes |
| Timing | Usually becomes apparent after birth | Usually present at birth |
| Resolution | Slower, often over weeks | Usually rapid |
| Main approach | Observation and complication monitoring | Observation and reassurance in an uncomplicated case |
Which scalp layer explains the suture rule?
Work from superficial to deep: skin and superficial tissues, the galea or epicranial aponeurosis, the subgaleal space, periosteum and cranial bone. The important comparison is between a collection above the galea, one beneath it, and one beneath the periosteum. Do not use “scalp swelling” as if it names a single compartment.

The subperiosteal plane explains cephalhaematoma. Periosteal attachment at the margins of a bone limits extension of the blood collection. Bilateral cephalhaematomas can occur as separate collections, so “swelling on both sides” is not the same as a continuous collection crossing the midline.
The subgaleal plane is deeper than caput and superficial to periosteum. It permits more extensive spread than a subperiosteal collection. That is why crossing sutures is not sufficient to diagnose benign caput. A deeper haemorrhage can also cross them and may carry a very different risk.
When do these swellings appear and how do they evolve?
Caput is typically evident at delivery because pressure during labour produces superficial oedema over the presenting scalp. It is often soft, boggy and poorly demarcated. A well newborn with a stable superficial swelling that crosses sutures fits the classic caput pattern, especially when the swelling improves quickly.
Cephalhaematoma may be absent or subtle immediately after birth because subperiosteal bleeding accumulates gradually. It commonly becomes most apparent in the first 1–3 days. The swelling may initially feel firm and become more fluctuant as time passes. The overlying scalp can move over the collection, and its border follows the affected bone.
| Observation | Supports | Reason |
|---|---|---|
| Diffuse swelling already evident at delivery | Caput in a well infant | Pressure-related superficial oedema |
| Localised swelling becomes clearer after delivery | Cephalhaematoma | Gradual subperiosteal blood accumulation |
| Rapid improvement, often within 48 hours | Uncomplicated caput | Oedema resolves promptly |
| Persistence over weeks | Cephalhaematoma | Clotted blood is absorbed more slowly |
| Progressive diffuse swelling with deterioration | Subgaleal haemorrhage concern | Potential ongoing blood loss in a large tissue plane |
Timing is useful but should not override contradictory findings. A collection that is clearly bounded by a suture remains anatomically different from continuous diffuse swelling. Similarly, an unwell infant needs urgent assessment even if caput was initially suspected. The diagnosis is based on the combined history, examination and evolution.
Which delivery factors increase the likelihood of scalp injury?
Labour applies pressure and shear forces to the fetal scalp and skull. Prolonged labour and instrumental delivery can increase the likelihood of scalp swelling or bleeding. Vacuum and forceps histories are relevant, but they do not by themselves identify which compartment contains the collection.
Cephalhaematoma develops when shear separates periosteum from the underlying bone and small vessels bleed into the new space. Caput reflects pressure-related superficial oedema. Subgaleal haemorrhage can follow damage to emissary veins beneath the galea. These different mechanisms explain why one birth history can accompany different scalp findings.
- Review the labour duration, presentation and use of instruments.
- Inspect and palpate the swelling rather than diagnosing from the delivery method alone.
- Record whether the collection has a clear boundary at a suture or spreads continuously.
- Reassess its size and the newborn’s clinical condition over time.
- Keep subgaleal haemorrhage in the differential when swelling is diffuse or progressive.
Parietal and occipital regions are common locations for cephalhaematoma. However, “parietal swelling after vacuum delivery” does not establish the diagnosis until the plane and boundaries are considered. The familiar exam association should direct inspection, not replace it.
How should an image or ultrasound question be approached?
In a schematic question, locate the skull and periosteum first. A collection between them is subperiosteal. A collection beneath the galea but outside the periosteum is subgaleal. A superficial oedematous swelling above the galea fits caput. This sequence is more reliable than choosing the diagnosis from the size or colour of the drawn bulge.
Ultrasound can help define the extracranial compartment when examination leaves uncertainty. Published point-of-care ultrasound cases illustrate the difference between a collection that stops at a suture and one that extends across it. The finding should be combined with the rest of the examination and the patient’s clinical state.
A high-frequency linear probe can show a superficial fluid collection and the deeper echogenic skull boundary. Scanning across a suspected suture is useful for demonstrating whether the collection continues. The cited report concerns differentiation of cephalhaematoma from subgaleal haematoma; it does not establish that every newborn scalp swelling requires ultrasound.
When are additional investigations useful?
Uncomplicated caput is generally diagnosed clinically and does not routinely require imaging. Cephalhaematoma is also usually a clinical diagnosis when its characteristic suture-limited boundary is clear. Imaging is selected for a specific concern, such as an underlying skull fracture, intracranial bleeding or uncertainty about the compartment.
Skull radiographs and CT can be considered when a fracture is suspected. Ultrasound or CT may help define the compartment and evaluate associated findings. The choice depends on the question being answered and the newborn’s condition. Do not convert a reference list of possible investigations into a rule that every infant needs all of them.
| Concern | Assessment direction | Exam distinction |
|---|---|---|
| Typical uncomplicated caput | Clinical observation | Routine imaging usually unnecessary |
| Suture-limited cephalhaematoma in a well newborn | Clinical monitoring, with targeted tests when indicated | A stable collection does not require routine drainage |
| Suspected skull fracture or intracranial injury | Targeted imaging selected by the clinical team | Extracranial swelling does not exclude associated injury |
| Diffuse progressive haemorrhage or circulatory compromise | Urgent clinical assessment and monitoring | Stabilisation takes priority over an elective diagnostic sequence |
A birth-injury stem may give a photograph, drawing or scan, but its final question can still be clinical. If it asks for the next step in an unwell infant, identifying the collection is only part of the answer. The consequences of bleeding and the need for urgent support matter as much as the anatomical label.
What complications should be monitored in cephalhaematoma?
Most cephalhaematomas resolve spontaneously, but breakdown of the collected blood can contribute to neonatal jaundice. Anaemia, infection, an associated skull fracture and persistent calcification or ossification are other recognised concerns. The examination often tests the link between an extracranial blood collection and bilirubin rather than the size of the lump alone.
Monitoring includes the clinical condition, evolution of the swelling and evidence of jaundice or other complications. Bilirubin assessment should follow the newborn’s clinical situation and local neonatal guidance. A cephalhaematoma does not define a universal bilirubin treatment threshold, because those decisions depend on age and other risk factors.
The collection can feel harder as blood calcifies during resolution, and the centre may flatten before the edges. Persistent or unusual changes warrant review rather than automatic reassurance. The general pattern of spontaneous recovery should be balanced with observation for the complications described in the source.
Caput has an excellent prognosis in uncomplicated cases and is usually managed by observation. Jaundice can also occur with scalp bruising or caput, so the comparison should not claim that jaundice is impossible in caput. The useful distinction is that cephalhaematoma contains a defined blood collection and commonly prompts attention to blood-breakdown effects.
Why is routine aspiration of cephalhaematoma avoided?
The usual management of an uncomplicated cephalhaematoma is observation. The blood often clots, so needle aspiration may be ineffective. Introducing a needle also creates a risk of infection and abscess. A large-looking swelling is therefore not, by itself, a reason to drain it.
Suspected infection is a different clinical problem and requires specialist evaluation. The recommendation to avoid routine aspiration should not be turned into a claim that investigation of an infected collection is never appropriate. For a straightforward exam stem involving a well newborn and a typical cephalhaematoma, expect conservative management with follow-up.
- Confirm the likely compartment and check for warning signs.
- Document the collection and review its evolution.
- Monitor for jaundice, anaemia and infection according to the clinical context.
- Explain the expected slower resolution compared with caput.
- Avoid routine aspiration or incision solely to reduce the visible swelling.
Caregiver counselling should include the expected course and reasons to seek review, such as increasing swelling, feeding difficulty, abnormal sleepiness or signs of infection. Clear expectations help prevent unnecessary manipulation of the collection while preserving attention to a change in the infant’s condition.
Why must subgaleal haemorrhage stay in the differential?
Subgaleal haemorrhage lies beneath the epicranial aponeurosis and outside the periosteum. It can cross sutures and spread extensively because the plane is not constrained to one cranial bone. Ruptured emissary veins can produce substantial bleeding into this space.
The danger is hypovolaemia and coagulopathy, with possible rapid deterioration. Diffuse swelling that progresses rather than resolves, particularly with signs of circulatory compromise, is not adequately explained by the reassuring caput pattern. The infant needs urgent neonatal assessment and support.
A question may deliberately provide “crosses sutures” as a tempting caput clue and then add increasing head swelling or shock. Re-read the systemic findings before selecting the answer. Caput and subgaleal haemorrhage share a boundary feature but differ in depth, contents and clinical consequences.